Traumatic brain injury (TBI) care has evolved significantly in the last decade. We are better at diagnosing the pattern of symptoms, better at teasing apart cognitive effects from psychiatric overlap, and far better at building personalised rehabilitation plans. Multidisciplinary input and realistic vocational support can genuinely improve lives.
However, there is a shortcoming that most clinicians, insurers, and personal injury lawyers recognise. Rehabilitation helps people adapt to disability, but it rarely reverses it. We have remained short of medical treatments that reliably shift the biology of the chronic post-TBI brain.
In January 2024, a paper in Nature Medicine introduced a protocol that challenges that limitation. It details a study of “Magnesium-Ibogaine” therapy. While the results are preliminary, they are generating intense interest because of the magnitude of the improvement reported.
The Unmet Need
The study, led by a team at Stanford University, addresses a clinical picture as common in road traffic accident victims as in veterans: the individual who sustained a TBI who is now trapped in a cycle of cognitive fog, PTSD, and functional decline.
Currently, there is no FDA or MHRA-approved therapy for the chronic disability that follows this kind of injury. Management leans on symptom control, such as antidepressants for mood, therapy for trauma, and strategies for memory. These are helpful, but they are rarely curative. The Stanford study asked a different question: Can a single, high-dose intervention reset the background state of the brain?
What the Data Actually Shows
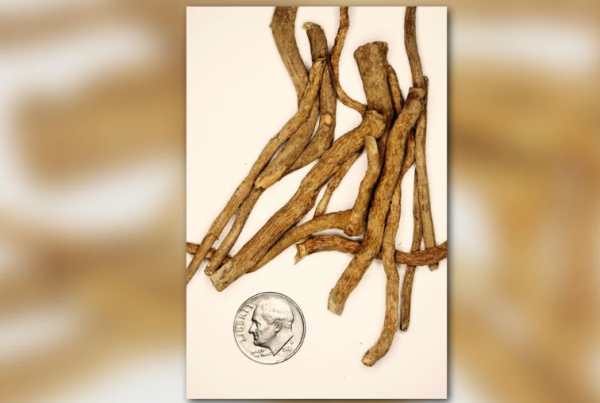
The researchers followed 30 US Special Operations veterans who travelled to Mexico to receive a single oral dose of ibogaine (a psychoactive alkaloid) co-administered with magnesium. The results were not subtle.
Disability vanished: The primary outcome was the WHODAS 2.0 disability score. At baseline, the group average was 30.2, indicating moderate-to-severe disability. One month after treatment, the average score had plummeted to 5.1, indicating no clinical disability.
Psychiatric remission: The study reported remission rates of over 83% for PTSD, depression, and anxiety.
Cognitive gains: The cohort showed measurable improvements in processing speed and executive function.
In the world of TBI research, where we often celebrate single-digit percentage improvements, an effect size this large is almost unheard of.
The Mechanism: How Could One Dose Work?
While the exact pharmacodynamics remain under investigation, current hypotheses suggest ibogaine acts as a “psychoplastogen”, a compound capable of physically regrowing neurons and promoting plasticity. Unlike daily antidepressants which work slowly, ibogaine appears to trigger a massive release of neurotrophic factors, specifically Glial Cell Line-Derived Neurotrophic Factor (GDNF) and Brain-Derived Neurotrophic Factor (BDNF). These proteins act as a fertiliser for neurons, encouraging the repair of damaged circuitry and the growth of new connections. Furthermore, ibogaine is known to block NMDA receptors, a mechanism shared with ketamine that can disrupt rigid, pathological neural patterns. The prevailing theory is that this combination reopens a “critical period” of plasticity similar to childhood learning states, allowing the brain to bypass damaged pathways and “reset” its functional connectivity in a way that traditional rehabilitation cannot.
The Safety Question
Why isn’t this already mainstream? The answer lies in risk and legality. Ibogaine is a powerful oneirogen (dream-inducing agent) associated with cardiotoxicity. In uncontrolled settings, it can cause fatal heart arrhythmias, specifically QT interval prolongation.
The study used magnesium to shield the heart, and in this carefully monitored group, there were no serious cardiac events. This suggests that the physical risks might be manageable under strict medical protocols, potentially transforming a “dangerous drug” into a viable clinical candidate.
Medico-Legal Real World
Before we rewrite the rehabilitation guidelines, we must apply a legal filter.
Legal Status: In the US, ibogaine is a Schedule I substance. In the UK, it is restricted under the Psychoactive Substances Act 2016. This makes supply and production illegal, preventing it from being prescribed. Any claimant accessing it would likely be doing so abroad, outside the governance of the GMC or NICE.
Study Limitations: This was an open-label study with no control group. The participants were elite veterans who were highly motivated and high-functioning prior to injury. This limits how much we can generalise the results to the wider civilian population.
The “Package” Effect: The treatment involved extensive coaching and preparation. We do not yet know how much of the recovery was due to the drug and how much was due to the holistic support.
Why This Matters Now
Despite the caveats, this paper represents a pivot point. It suggests that the chronic sequelae of TBI, often viewed as permanent structural deficits, may actually be functional states that can be treated.
If future randomised controlled trials reproduce these results, the implications for personal injury claims are profound. It moves the discussion from ‘how much care will this claimant need for life?’ to ‘is there a curative intervention we should be funding?’
We are not there yet. But for the first time in years, the door to reversing chronic TBI disability looks slightly ajar.
Key Takeaways
The Study: A 2024 Stanford study showed that a single dose of magnesium-ibogaine significantly reduced disability and psychiatric symptoms in veterans with TBI.
The Effect: Average disability scores dropped from 30.2 (moderate-severe) to 5.1 (no disability) within one month.
The Caveat: Ibogaine is not licensed for medical use in the UK and carries known cardiac risks. The study lacked a control group and relied on elite military participants.
The Future: If replicated in larger trials, this could shift the focus of TBI claims from lifetime management to curative intervention.
References
Cherian KN, Keynan JN, Anker L, et al. Magnesium–ibogaine therapy in veterans with traumatic brain injuries. Nature Medicine. 2024;30:373–381.